


Introduction: the current epidemic of COVID-19 requires a lot of efforts to be controlled involving pharmacotherapy and clinical pharmacology studies. Aim: to introduce a brief review of drugs under investigation for COVID-19.
Methodology: Our project is a systematic review of many medications being studied for their effectiveness and safety in COVID-19 management.
Results: Antiviral drugs (osletmivir, ramdisvir), corticosteroids (dexamethasone), immunomodulators (anakinera, toculizumab), antithrombotic (antiplatletes, anticoagulants) are still under investigation although preliminary results are promising.
Conclusion: Yet, few medications have been approved by FDA for management of COVID-19 but drugs have been used in clinical trials under FDA emergency use authorization. Ongoing clinical trials are essential to establish their long-term safety and effectiveness. Key points: 1. Scientists are testing different medicines, such as antivirals, steroids, immune-boosting drugs, and blood thinners, to see if they can help treat COVID-19. 2. Some of these drugs show early promise, but only a few have official approval for use. 3. More research and clinical trials are needed to make sure these treatments are safe and work well in the long run.
Share on Mobile
Scan to access on mobile
Keywords
COVID-19
Antiviral therapy
Corona virus
INTRODUCTION
Coronaviruses (CoVs) are a family of RNA viruses classified under the subfamily Orthocoronavirinae, within the Coronaviridae family and the order Nidovirales. This group includes alpha-, beta-, gamma-, and delta-coronaviruses. Notably, beta-coronaviruses have been responsible for three major outbreaks in the past two decades: Severe Acute Respiratory Syndrome (SARS-CoV) in 2002, Middle East Respiratory Syndrome (MERS-CoV) in 2012, and the ongoing COVID-19 pandemic caused by SARS-CoV-2, first identified in late 2019 (Banerjee et al., 2019; The Lancet Oncology, 2020).
As of July 31, 2020, the World Health Organization (WHO) had received extensive global reporting on COVID-19 cases ( (Figure 1); World Health Organization, 2020). These data underscore the importance of robust clinical and pharmacological responses to curb the pandemic.
Objectives
To introduce a brief review of medications under investigation for COVID-19 management showing their efficacy and safety with evidence by clinical trials
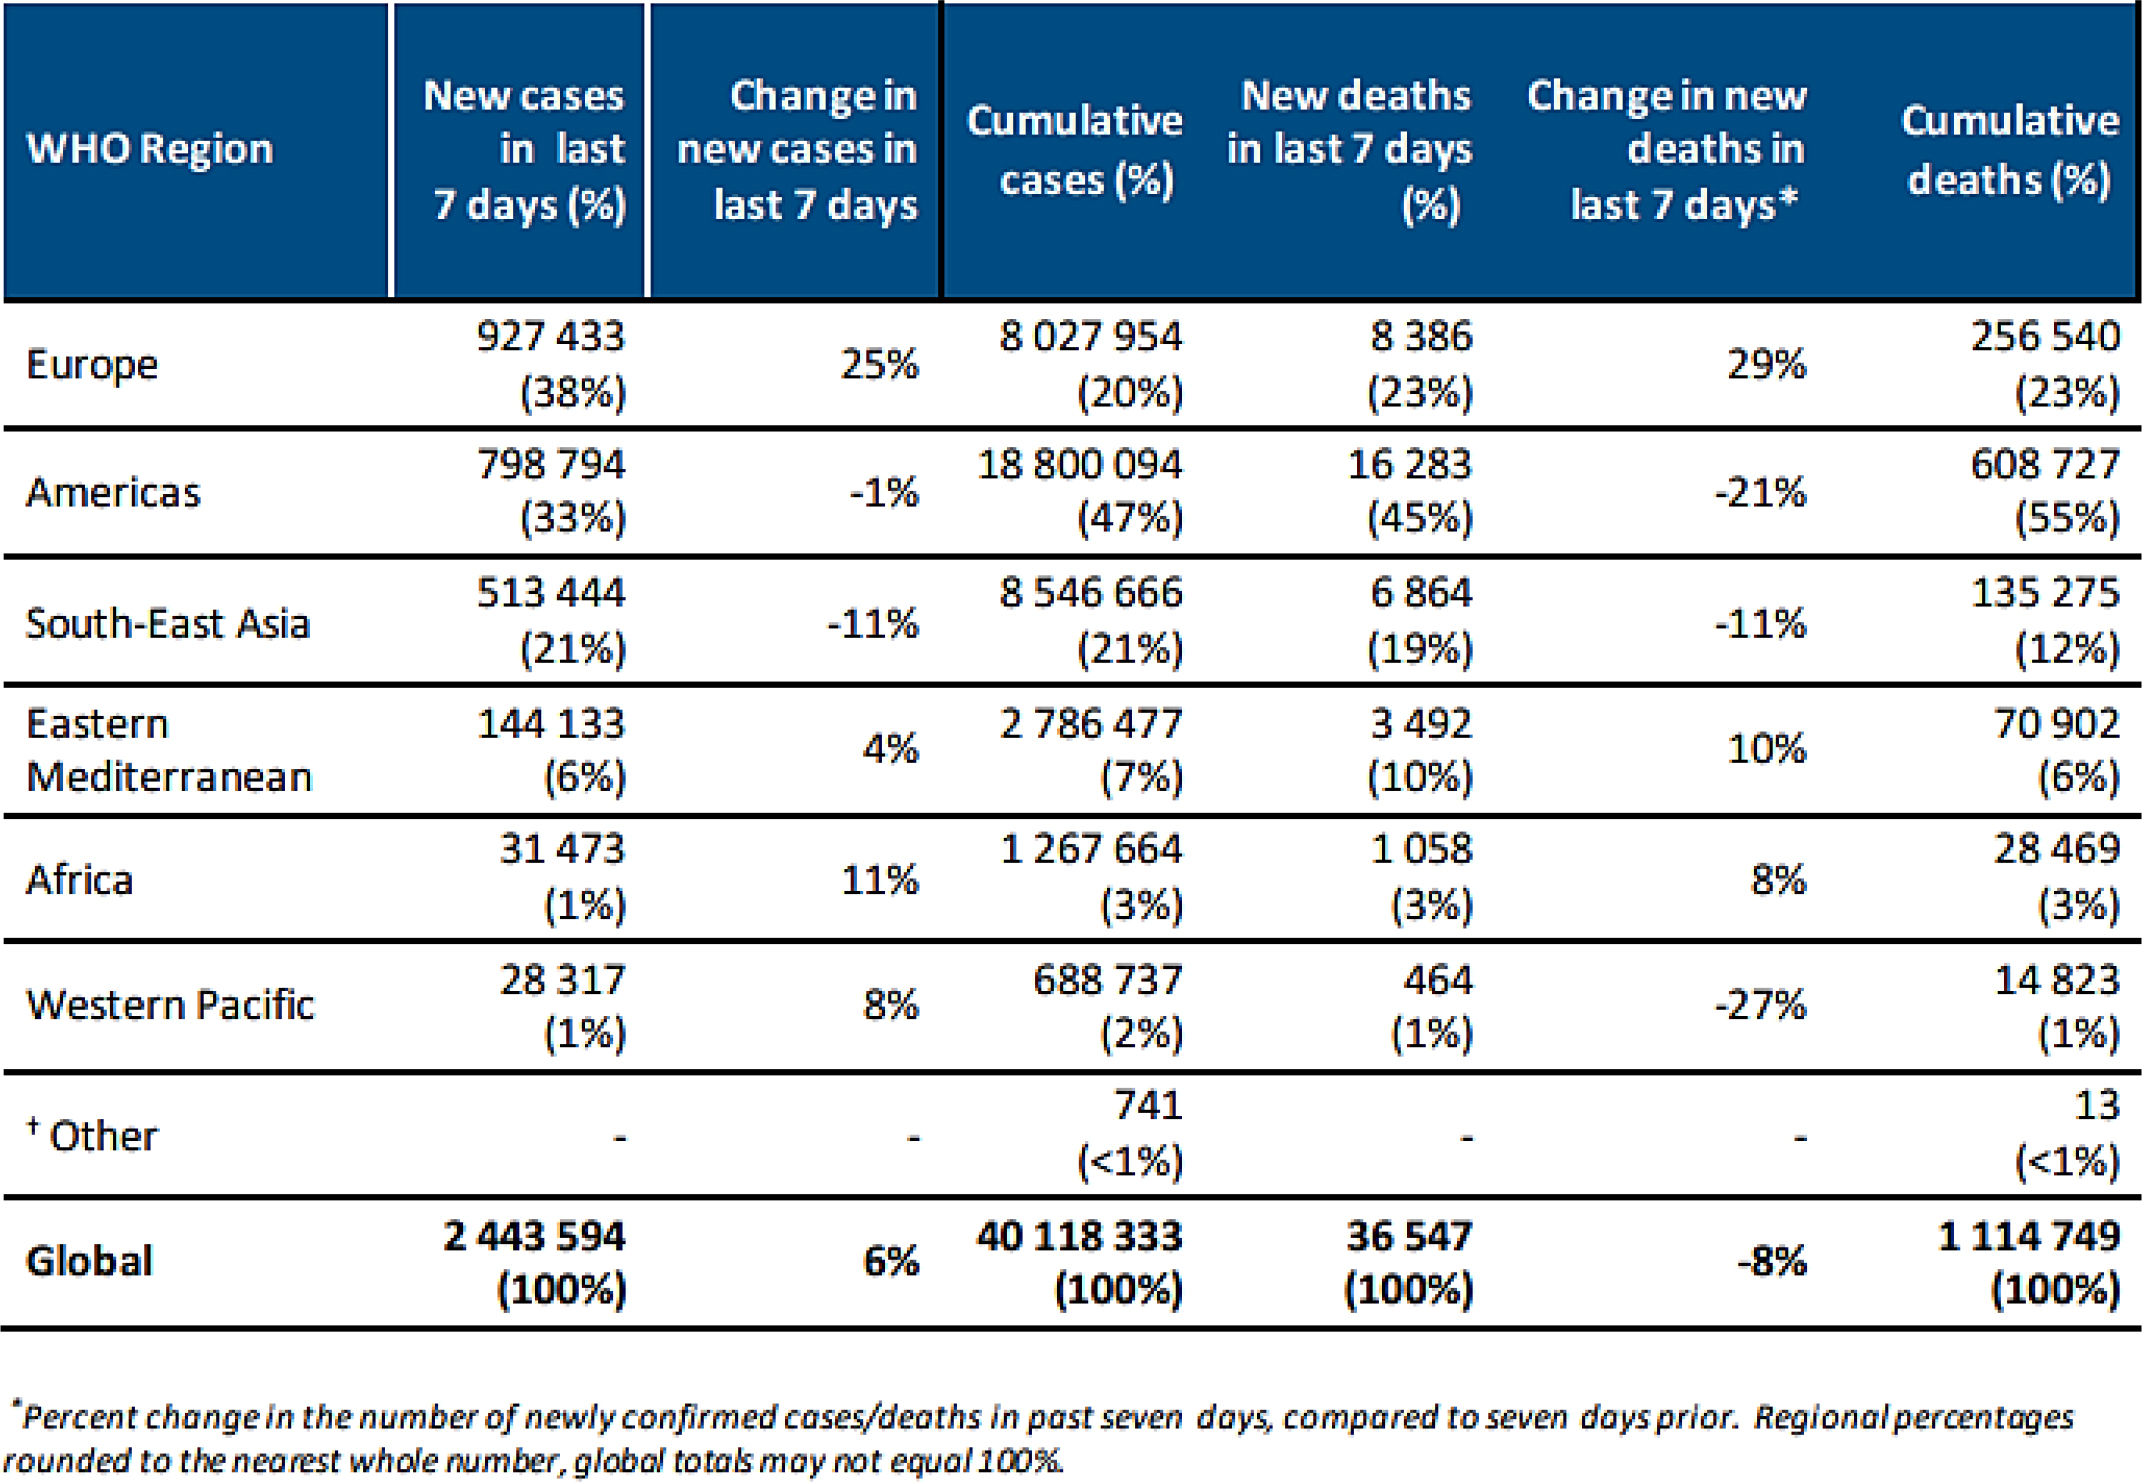
Figure 1: COVID-19 Situation in numbers 20/10/2020 (by WHO Region) (Al-Tawfiq et al., 2014).
METHODOLOGY
Our study is a systematic review of many medications being studied for their effectiveness and safety in COVID-19 management. We used PubMed search tool using term "management of COVID-19 by pharmacotherapy" resulting in many clinical trials and few systematic review.
Literature Review
Coronavirus‐specific treatments
Coronavirus‐specific treatments are shown in Figures 3 and 4 shows a recommendation rating scheme.
Chloroquine/Hydroxychloroquine
These antimalarial compounds initially showed promise due to their ability to interfere with viral entry via the ACE2 receptor. However, data from clinical trials have yielded inconsistent efficacy and raised concerns over cardiac safety, particularly QT interval prolongation, limiting their use to experimental settings (Savarino et al., 2003; Vincent et al., 2005; Fang et al., 2020; Borba et al., 2020; CredibleMeds, 2020; Rosa and Santos, 2020; Chorin et al., 2020).
Promazine
As an older antipsychotic, promazine has demonstrated potential antiviral activity by disrupting the viral entry process, but it has not progressed beyond preclinical evaluation (Zhang and Yap, 2004).
Antiviral treatments
Summary of antiviral agents is shown in Figures 5-7.
Lopinavir/ritonavir (Kaletra)
This protease inhibitor combination, used in HIV management, showed modest efficacy in early coronavirus outbreaks. Its use in COVID-19 has been discouraged outside clinical trials due to pharmacokinetic challenges and limited clinical improvement (Tsang and Zhong, 2003; Kim et al., 2016; Cao et al., 2020).
Remdesivir
A nucleotide analog with broad antiviral properties, remdesivir has demonstrated inhibition of coronavirus replication in animal and human studies. It is frequently administered to hospitalized patients requiring respiratory support, typically in a 5- to 10-day course depending on clinical status (Agostini et al., 2018; Sheahan et al., 2020; Beigel et al., 2020; Goldman et al., 2020).
Nelfinavir
Another HIV medication, nelfinavir has shown in vitro suppression of SARS-CoV replication and is being considered for further exploration against COVID-19 (Yamamoto et al., 2004).
Azithromycin
Known for its anti-inflammatory and immunomodulatory effects, azithromycin has been combined with hydroxychloroquine in early studies. However, this regimen has not shown consistent benefits and may increase cardiac risks (Gautret et al., 2020; Molina et al., 2020).
Niclosamide and Ivermectin
These antiparasitic agents have shown antiviral activity in vitro. Ivermectin, in particular, has demonstrated a rapid reduction in viral RNA levels, but clinical evidence remains limited (Wu et al., 2004; Caly et al., 2020).
Oseltamivir
Primarily used for influenza, oseltamivir has been included in some investigational combinations against COVID-19, although its individual efficacy remains unclear (Rosa and Santos, 2020).
Immune-Based Therapy Under Evaluation for Treatment of COVID-19
Interleukin-1 Inhibitors
Medications like anakinra, which target IL-1, are being investigated for their potential in managing COVID-19-related inflammation. However, data remain insufficient to recommend their use outside of clinical trials (Shakoory et al., 2016; Aouba et al., 2020; Cavalli et al., 2020).
Interleukin-6 Inhibitors
Agents such as tocilizumab, sarilumab, and siltuximab target IL-6 pathways involved in cytokine release syndromes. Despite their theoretical benefits, current evidence is inadequate to suggest routine use in COVID-19 (Press Release, 2020; Sciascia et al., 2020).
Interferons (Alfa, Beta)
The COVID-19 Treatment Guidelines Panel advises against the use of interferons in COVID-19 management except within the context of formal clinical trials (Al-Tawfiq et al., 2014; Arabi et al., 2019).
Janus Kinase Inhibitors (e.g., Baricitinib)
JAK inhibitors, including baricitinib, are not currently recommended for general COVID-19 treatment and should only be administered under controlled clinical research (Richardson et al., 2020).
Antithrombotic Therapy in Patients with COVID-19
Venous Thromboembolism Prophylaxis and Screening
Non-hospitalized individuals with COVID-19 should not receive anticoagulation prophylaxis unless another indication exists (AIII). Hospitalized patients should receive standard VTE prophylaxis, but routine post-discharge prophylaxis is not recommended unless specific high-risk factors apply (BI).
Screening and Management
Routine screening for thrombotic events in asymptomatic COVID-19 patients is not supported by current evidence (BIII). However, if there is rapid clinical deterioration suggestive of thromboembolism, further evaluation and management are warranted (AIII).
Treatment
In cases of confirmed or highly suspected thromboembolism where imaging is not feasible, standard anticoagulant therapy should be initiated (AIII). Patients undergoing ECMO, CRRT, or catheter-based interventions should also receive antithrombotic therapy as per institutional protocols (AIII).
Selection of Anticoagulant or Antiplatelet Drugs for Patients with COVID-19
For hospitalized patients, low molecular weight or unfractionated heparin is preferred due to better control and fewer interactions (AIII). Outpatients on warfarin with limited INR access may transition to direct oral anticoagulants unless contraindicated (American Society of Hematology, 2020).
Other compounds
Dexamethasone
As a potent corticosteroid, dexamethasone has shown benefit in reducing inflammation and improving outcomes in patients with severe COVID-19. The RECOVERY trial demonstrated improved survival among ventilated patients or those needing supplemental oxygen (Horby et al., 2020). Dexamethasone is not advised in cases without oxygen support (AI) (Molina et al., 2020). Chronic corticosteroid users for underlying conditions should continue therapy, possibly with stress-dose adjustments (AIII) (Kaiser et al., 2020).
Empiric Broad-Spectrum Antimicrobial Therapy
In patients with COVID-19 and intense or vital illness, there are inadequate records to endorse empiric broad-spectrum antimicrobial therapy in the absence of any other indication (BIII).
If antimicrobials are initiated, the Panel recommends that their use must be reassessed every day so that you can decrease the unfavorable effects of needless antimicrobial therapy (AIII).
Considerations for Certain Concomitant Medications in Patients with COVID-19
Ibuprofen
Ibuprofen, a Nonsteroidal Anti-Inflammatory Drug (NSAID), is an activator of ACE2 receptors, similar to ACE inhibitors or ARBs. Their utilization can result in an increased hazard of contracting COVID-19 (Fang et al., 2020). Since fatal lung failure triggered through SARS-CoV infections can be managed through blocking the renin-angiotensin pathway (Kuba et al., 2005), ibuprofen might not be harmful. However, there is no strong evidence suggesting a link between NSAID use and worsening symptoms due to SARS-CoV-2 infection.
Indomethacin
Amici et al., (2006) demonstrated that indomethacin, a widely used NSAID and a potential Cyclooxygenase (COX) inhibitor, exhibits antiviral activity against SARS-CoV. Remarkable inhibition of SARS-CoV-infected cells by more than 99% at non-toxic concentrations was also observed. This suggests probable efficacy of indomethacin against SARS-CoV-2.
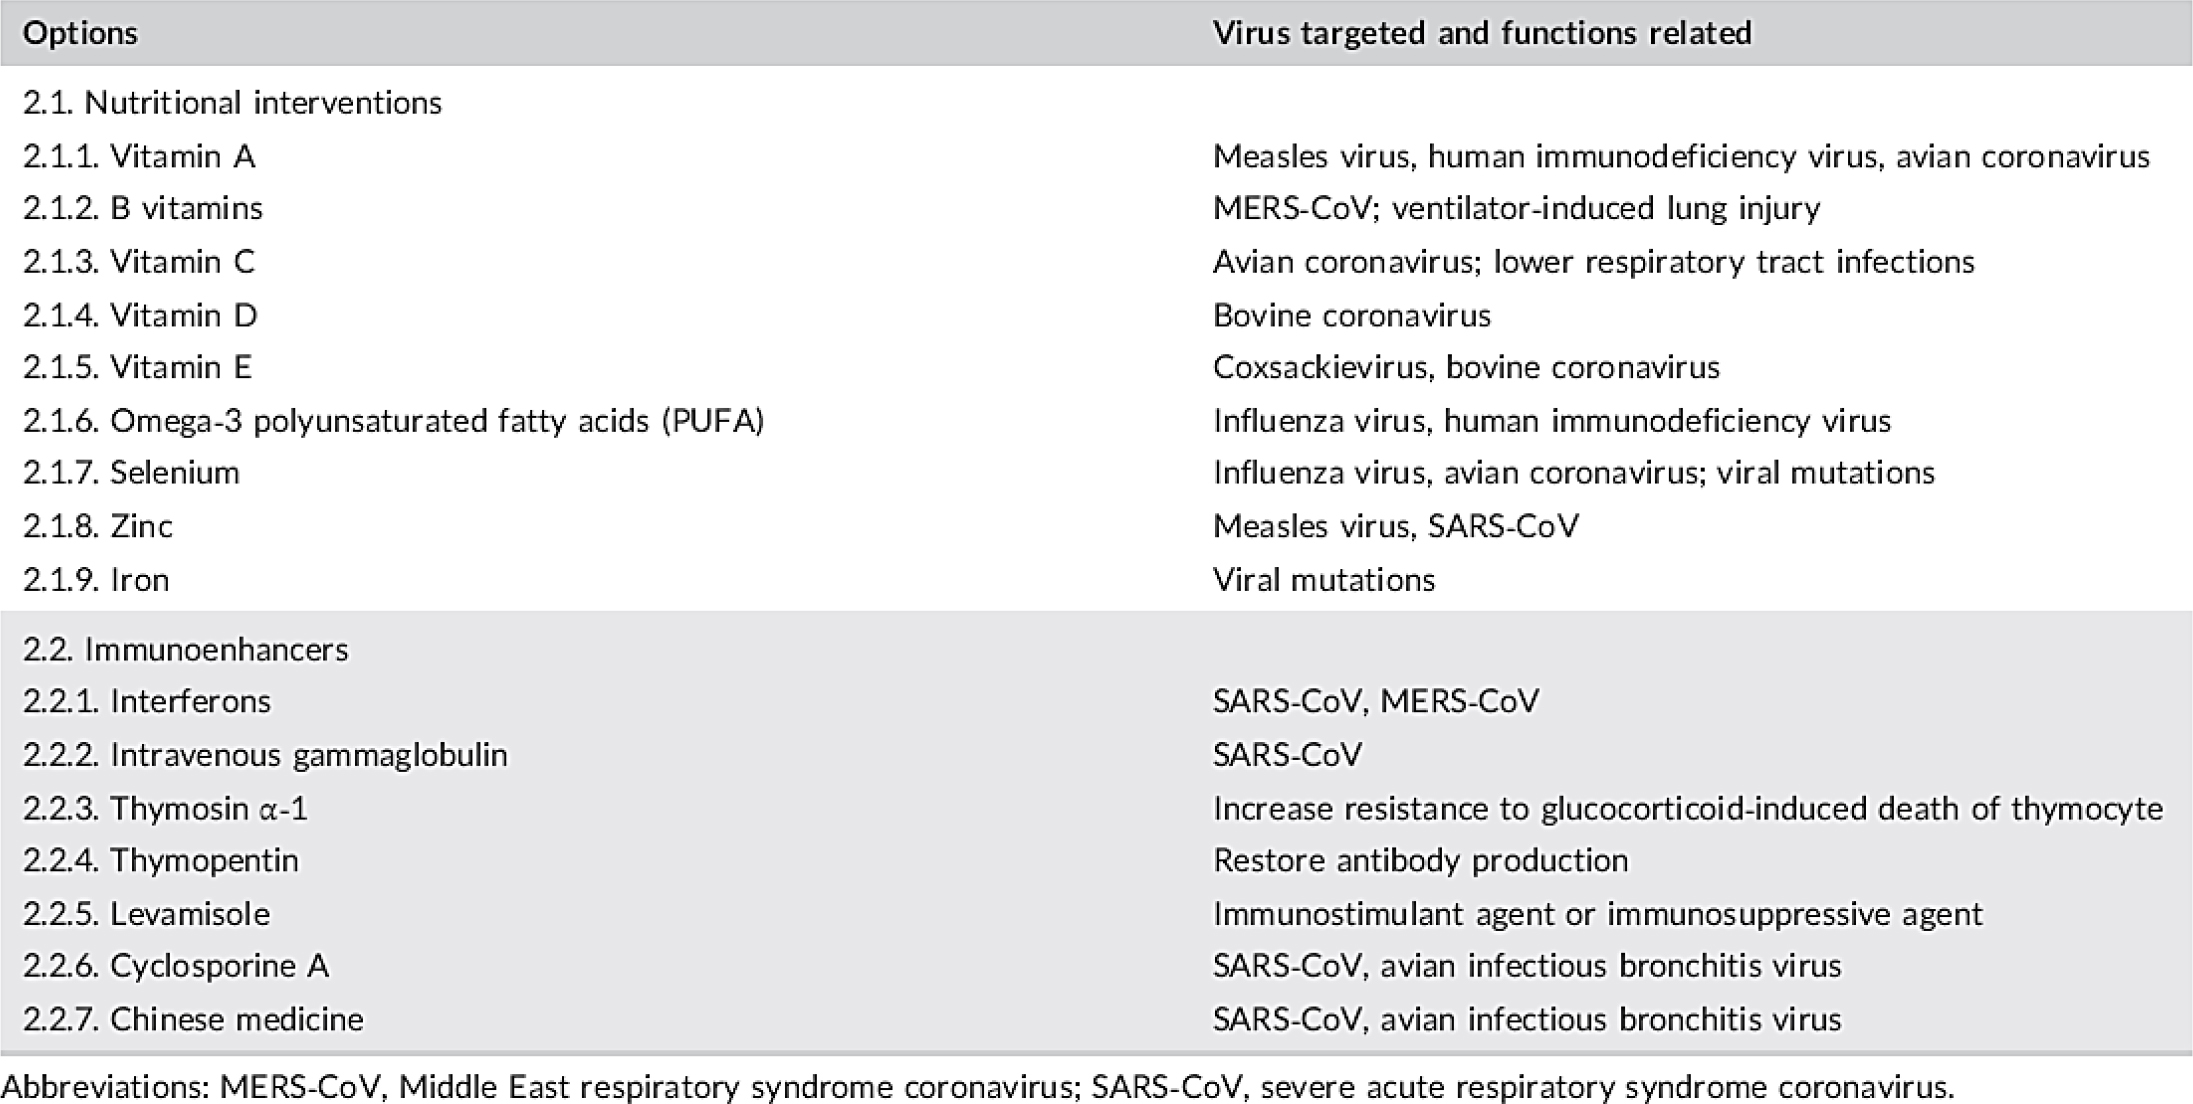
Figure 2: General supportive treatments of COVID-19 (Amici et al., 2006).
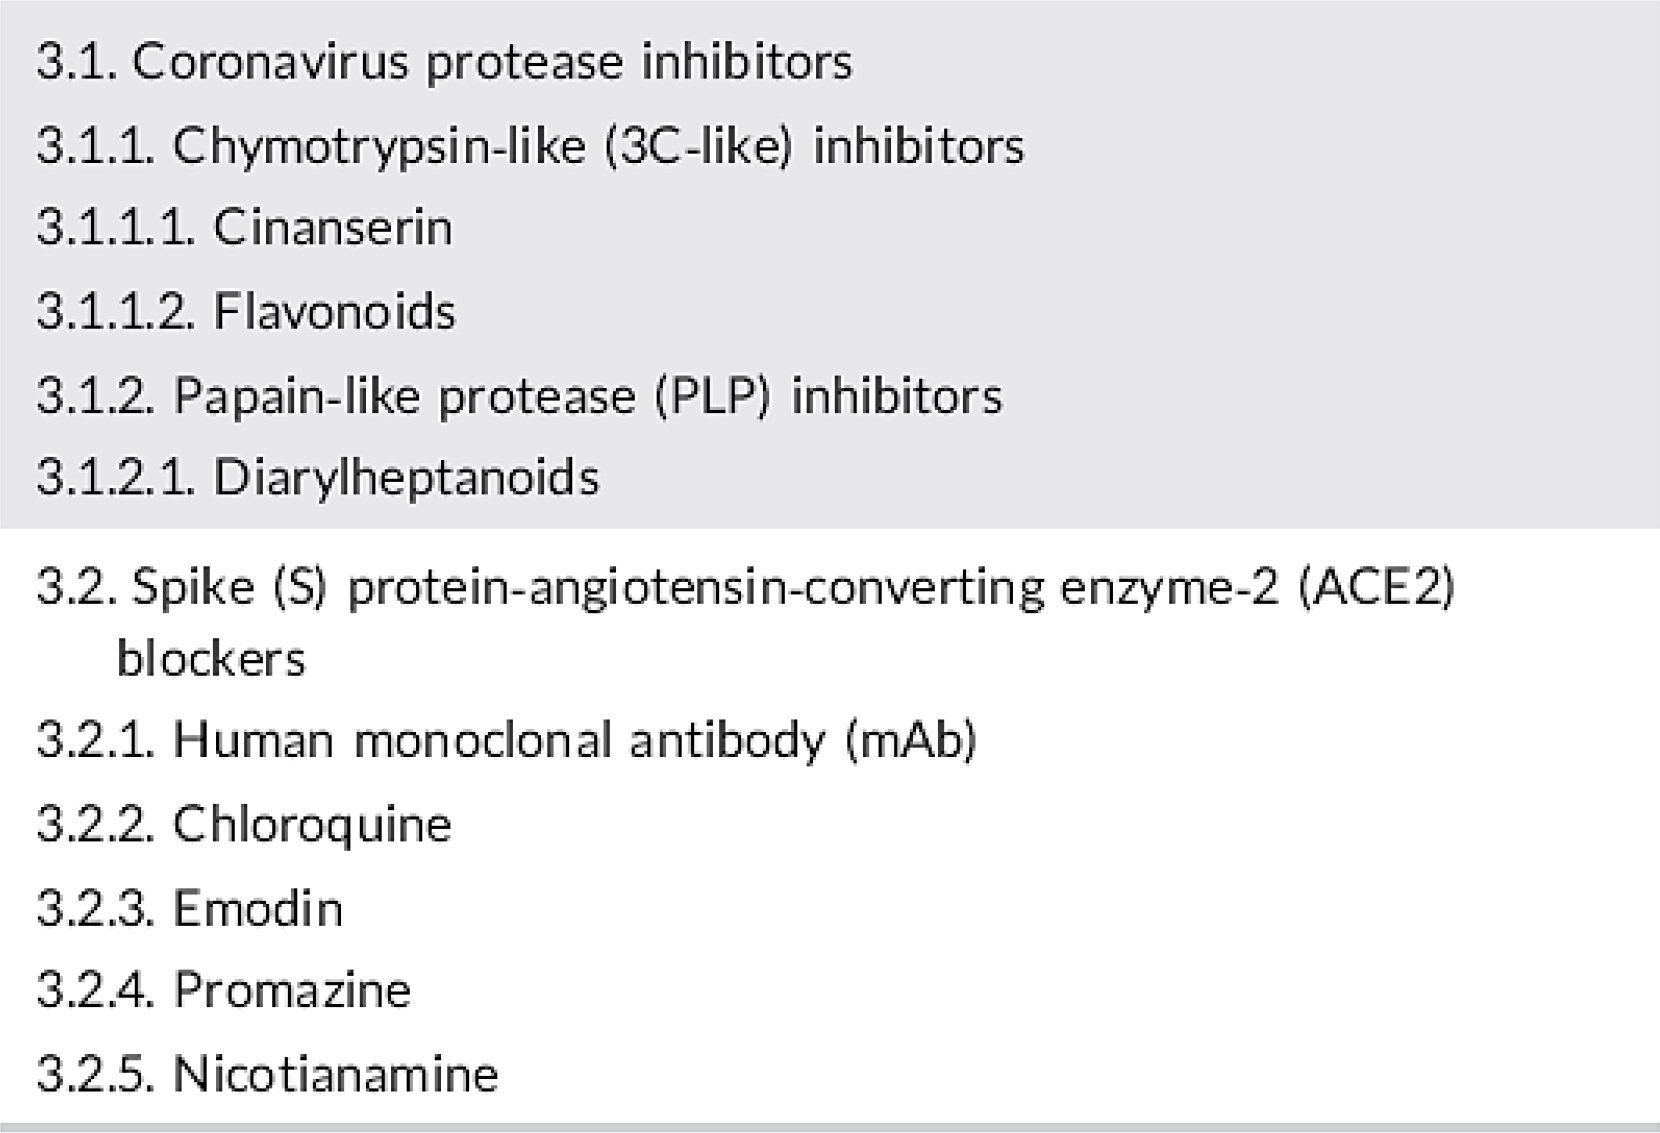
Figure 3: Coronavirus‐specific treatments (Amici et al., 2006).
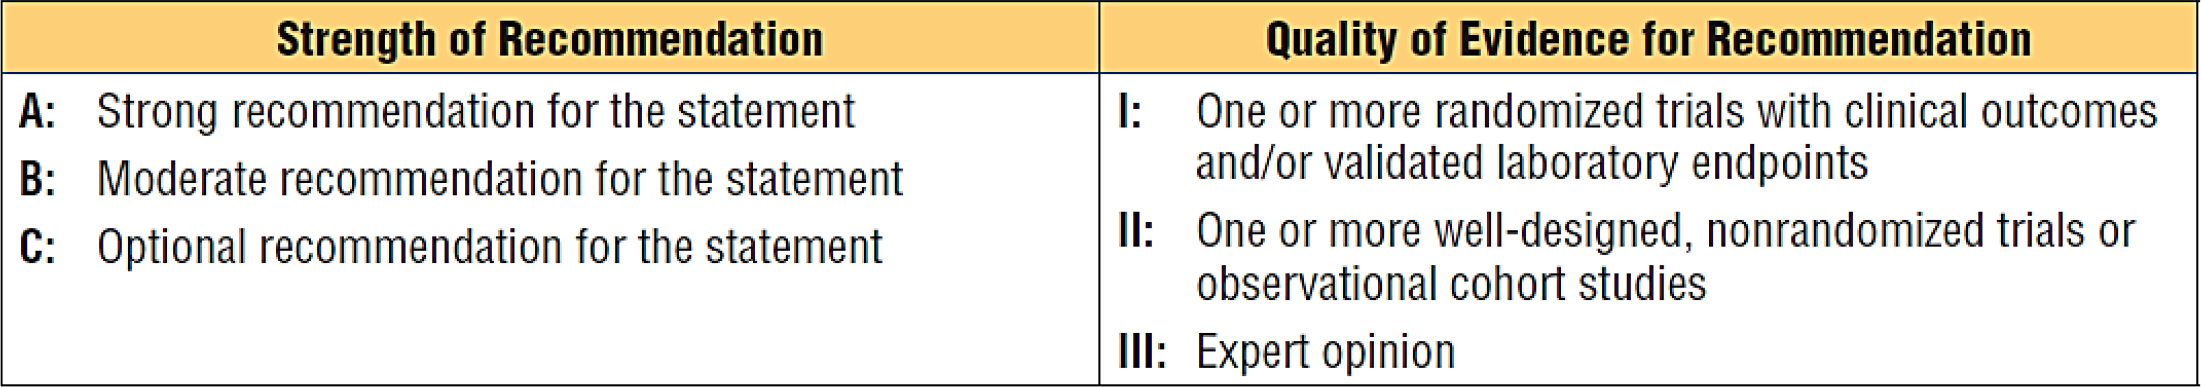
Figure 4: Recommendation Rating Scheme.

Figure 5: Antiviral drugs for COVID-19.

Figure 6: Characteristics of Potential Antiviral Agents Under Evaluation for COVID-19 (Food and Drug Administration, 2020).

Figure 7: Characteristics of Immune-Based Therapy Under Evaluation for Treatment of COVID-19 (Food and Drug Administration, 2020).
RESULTS
Nutritional intervention: Vitamins, minerals, and immunomodulators play an important role in enhancing the body’s immunity against several viruses, including SARS-CoV (Zhang and Liu, 2020). Chloroquine and hydroxychloroquine are potent inhibitors of SARS coronavirus infection but are not recommended for use outside clinical trials (Savarino et al., 2003).
Currently, many trials are testing the effect of azithromycin in conjunction with hydroxychloroquine on the course of disease in people with SARS-CoV-2, showing its efficacy (Gautret et al., 2020; Molina et al., 2020). However, the azithromycin and hydroxychloroquine combination is not recommended for use outside clinical trials due to potential interactions (e.g., prolonged QT-interval) (Borba et al., 2020; CredibleMeds, 2020; Rosa and Santos, 2020).
Although lopinavir/ritonavir showed potential during the early disease phase in conjunction with interferons, studies have since shown limited benefit in COVID-19 patients due to poor pharmacokinetics (Cao et al., 2020).
Remdesivir has shown efficacy in preclinical studies by reducing viral load and improving lung function. It is currently recommended for hospitalized patients requiring oxygen or mechanical support (Agostini et al., 2018; Sheahan et al., 2020; Beigel et al., 2020).
Nelfinavir has also demonstrated significant inhibitory effects on SARS-CoV replication and may be a candidate for further COVID-19 trials (Yamamoto et al., 2004). Oseltamivir, while effective against influenza, is being studied in combination with other drugs for potential use against SARS-CoV-2 (Rosa and Santos, 2020).
Niclosamide and ivermectin both show strong in vitro antiviral properties, with ivermectin reducing viral RNA by thousands-fold within 48 hr (Caly et al., 2020; Wu et al., 2004).
ALA acts as an antioxidant, potentially reducing oxidative stress and related complications during viral infection, including COVID-19 (Tibullo et al., 2017; Wu et al., 2008).
Dexamethasone has proven clinical benefit in patients requiring respiratory support by dampening systemic inflammation (Horby et al., 2020).
Use of broad-spectrum antibiotics is discouraged unless secondary infection is suspected. Convalescent plasma, IL-1/IL-6 inhibitors, interferons, and baricitinib remain under investigation and are not yet recommended for routine care (Ahn et al., 2020; Shakoory et al., 2016; Cavalli et al., 2020; Sciascia et al., 2020; Al-Tawfiq et al., 2014; Richardson et al., 2020).
Convalescent Plasma and Immune Globulins
There are insufficient data to recommend either for or against the use of COVID-19 convalescent plasma or SARS-CoV-2 immune globulins for the treatment of COVID-19 (Ahn et al., 2020; Ye et al., 2020; Zeng et al., 2020).
Antithrombotic Therapy
Antithrombotic interventions, including heparins and oral anticoagulants, are used only when clinically indicated. Choice of drug depends on the patient’s condition and setting, with LMWH and UFH preferred in hospitalized patients (American Society of Hematology, 2020).
Anakinra
There are insufficient data to recommend either for or against the use of interleukin-1 (IL-1) inhibitors, such as anakinra, for the treatment of COVID-19 (Aouba et al., 2020; Cavalli et al., 2020).
Tocilizumab
There are insufficient data to recommend either for or against the use of interleukin-6 (IL-6) inhibitors (tocilizumab) for the treatment of COVID-19 (Press Release, 2020; Sciascia et al., 2020).
Interferons
It is not recommended to use interferons for the treatment of COVID-19, except in the context of a clinical trial (Al-Tawfiq et al., 2014; Arabi et al., 2019).
Baricitinib
It is not recommended to use Janus kinase (JAK) inhibitors (e.g., baricitinib) for the treatment of COVID-19, except in the context of a clinical trial (Richardson et al., 2020).
Antithrombotic Therapy
Patients with COVID-19 who experience an incident thromboembolic event or who are highly suspected to have thromboembolic disease at a time when imaging is not possible should be managed with therapeutic doses of anticoagulant therapy as per the standard of care for patients without COVID-19. Patients with COVID-19 who require extracorporeal membrane oxygenation or continuous renal replacement therapy or who have thrombosis of catheters or extracorporeal filters should be treated with antithrombotic therapy per institutional protocols. Low molecular weight heparin or unfractionated heparin may be preferred in hospitalized, critically ill patients because of their shorter half-lives, ability to be administered intravenously or subcutaneously, and fewer drug-drug interactions compared with oral anticoagulants. Outpatients receiving warfarin who are unable to get international normalized ratio monitoring during isolation may be candidates for direct oral anticoagulant therapy. Patients with mechanical heart valves, ventricular assist devices, valvular atrial fibrillation, or antiphospholipid antibody syndrome or patients who are lactating should continue treatment with warfarin therapy (American Society of Hematology, 2020).
Angiotensin-Converting Enzyme (ACE) Inhibitors and Angiotensin Receptor Blockers (ARBs)
It is not recommended to use ACE inhibitors or ARBs for the treatment of COVID-19 outside the setting of a clinical trial (Patel and Verma, 2020).
HMG-CoA Reductase Inhibitors (Statins)
It is not recommended to use statins for the treatment of COVID-19 outside the setting of a clinical trial (Fedson et al., 2020).
Nonsteroidal Anti-Inflammatory Drugs (NSAIDs)
There should be no difference in the use of antipyretic strategies (e.g., with acetaminophen or NSAIDs) between patients with or without COVID-19 (Food and Drug Administration, 2020; Bancos et al., 2009).
Ibuprofen is an activator of ACE2 receptors; its usage can lead to increased risk of contracting COVID-19 (Fang et al., 2020).
Indomethacin
Indomethacin exhibits antiviral activity against SARS-CoV. Remarkable inhibition against SARS-CoV-infected Vero cells by more than 99% at concentrations that were non-toxic for uninfected cells has also been observed. This suggests probable efficacy of indomethacin against SARS-CoV-2 (Amici et al., 2006).
DISCUSSION
As shown in our results, clinical trials are still in progress and until now there are no definitive results for the efficacy of studied medications for management of COVID-19. Although preliminary findings for some medications are promising, others show that harms may outweigh benefits.
Nutritional interventions should be initiated as early as diagnosis is suspected to enhance patient immunity against respiratory viruses and any opportunistic bacterial respiratory infections (Zhang and Liu, 2020).
Chloroquine, hydroxychloroquine, lopinavir/ritonavir, anakinra, tocilizumab, interferons, baricitinib, ACE inhibitors, ARBs, and statins are still not recommended for COVID-19 management except in clinical trials (Vincent et al., 2005; Cao et al., 2020; Aouba et al., 2020; Cavalli et al., 2020; Sciascia et al., 2020; Al-Tawfiq et al., 2014; Arabi et al., 2019; Richardson et al., 2020; Patel and Verma, 2020; Fedson et al., 2020).
Remdesivir, nelfinavir, azithromycin, niclosamide, ivermectin, oseltamivir, indomethacin, convalescent plasma, and immune globulins have shown antiviral activity against SARS-CoV-2, though clinical trials are still in progress (Rosa and Santos, 2020; Beigel et al., 2020; Caly et al., 2020; Wu et al., 2004; Amici et al., 2006; Ahn et al., 2020; Ye et al., 2020).
Dexamethasone has shown improvement in COVID-19 patients who developed Systemic Inflammatory Response Syndrome (SIRS) and pulmonary inflammation (Horby et al., 2020).
ALA, due to its antioxidant effects, may help mitigate complications linked to viral oxidative stress (Tibullo et al., 2017; Wu et al., 2008).
Antithrombotic therapy is not used unless there is a clear indication for either prophylaxis or treatment. Low Molecular Weight Heparin (LMWH) or Unfractionated Heparin (UFH) are favored for critically ill patients, while Direct Oral Anticoagulants (DOACs) or warfarin are appropriate for stable outpatients when monitoring is feasible (American Society of Hematology, 2020).
For hospitalized, critically ill patients, LMWH or UFH may be preferred because of their shorter half-lives, intravenous or subcutaneous administration, and fewer drug-drug interactions compared with oral anticoagulants. For outpatients, warfarin or DOACs are preferred. In cases where international normalized ratio monitoring is not possible during isolation, DOAC therapy is recommended. Patients with mechanical heart valves, ventricular assist devices, valvular atrial fibrillation, or antiphospholipid antibody syndrome or lactating patients should continue warfarin therapy (American Society of Hematology, 2020).
CONCLUSION
Finally, treating physicians should consider patients' co-morbidities and efficacy of medications used in patient management. Cardiac patients taking antiarrhythmic drugs should avoid medications causing QT-interval prolongation (azithromycin, chloroquine and hydroxychloroquine). Corticosteroids using in hypertensive and diabetic patients require monitoring BP and RBG. Nutritional interventions (ex: vitamin C and zinc) have important role in enhanching immunity against viral infection on long term use.
Medications that show antiviral activity against COVID-19, have proven benefits in SARS-COV2 management (remedisvir, nilfenvir, oseltamvir, azithromycin, ivermectin, niclosamid). Corticosteroids improve SIRS and respiratory symptoms associated with COVID-19 infection.
ALA has antioxidant activity and prevents oxidative stress and neuropathy associated with viral infection.
Anti-thrombotic therapy is used only when there is an indication for its use whether treatment or prophylaxis. Injectable anticoagulants are preferred in hospitalized patients while warfarin and direct oral anticoagulants are preferred in outpatients.
Other medications still do not show benefits in COVID-19 management and their use is limited to clinical trials (Chloroquine, hydroxychloroquine, Lopinavir/ritonavir, anakinra, tocilizumab, Interferons, Baricitinib, ACEIs, ARBs and statins).
References
Ahn, J. Y., Sohn, Y., Lee, S. H. (2020). Use of convalescent plasma therapy in two COVID-19 patients with acute respiratory distress syndrome in Korea. Journal of Korean Medical Science, 35(14), e149. https://doi.org/10.3346/jkms.2020.35.e149
Agostini, M. L., Andres, E. L., Sims, A. C., Graham, R. L., Sheahan, T. P., Lu, X. (2018). Coronavirus susceptibility to the antiviral remdesivir (GS-5734) is mediated by the viral polymerase and the proofreading exoribonuclease. mBio, 9(2), e00221-18. https://doi.org/10.1128/mBio.00221-18
Al-Tawfiq, J. A., Momattin, H., Dib, J., Memish, Z. A. (2014). Ribavirin and interferon therapy in patients infected with the Middle East respiratory syndrome coronavirus: An observational study. International Journal of Infectious Diseases, 20, 42-46. https://doi.org/10.1016/j.ijid.2013.12.003
Amici, C., Di Caro, A., Ciucci, A., Chiappa, L., Castilletti, C., Martella, V. (2006). Indomethacin has a potent antiviral activity against SARS coronavirus. Antiviral Therapy, 11(8), 1021-1030.
(2020). HFSA/ACC/AHA statement addresses concerns re: using RAAS antagonists in COVID-19..
(2020). COVID-19 and VTE/anticoagulation: Frequently asked questions..
Aouba, A., Baldolli, A., Geffray, L. (2020). Targeting the inflammatory cascade with anakinra in moderate to severe COVID-19 pneumonia: Case series. Annals of the Rheumatic Diseases, 79(10), 1381-1382. https://doi.org/10.1136/annrheumdis-2020-217706
Arabi, Y. M., Shalhoub, S., Mandourah, Y. (2019). Ribavirin and interferon therapy for critically ill patients with Middle East respiratory syndrome: A multicenter observational study. Clinical Infectious Diseases, 70(9), 1837-1844. https://doi.org/10.1093/cid/ciz544
Banerjee, A., Kulcsar, K., Misra, V., Frieman, M., Mossman, K. (2019). Bats and coronaviruses. Viruses, 11(1), 41. https://doi.org/10.3390/v11010041
Bancos, S., Bernard, M. P., Topham, D. J., Phipps, R. P. (2009). Ibuprofen and other widely used non-steroidal anti-inflammatory drugs inhibit antibody production in human cells. Cellular Immunology, 258(1), 18-28. https://doi.org/10.1016/j.cellimm.2009.03.008
Beigel, J. H., Tomashek, K. M., Dodd, L. E., Mehta, A. K., Zingman, B. S., Kalil, A. C. (2020). Remdesivir for the treatment of Covid-19 — Preliminary report. New England Journal of Medicine, 383(19), 1813-1826. https://doi.org/10.1056/NEJMoa2007764
Borba, M. G. S., Val, F. F. A., Sampaio, V. S. (2020). Effect of high vs low doses of chloroquine diphosphate as adjunctive therapy for patients hospitalized with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) infection: A randomized clinical trial. JAMA Network Open, 3(4), e208857. https://doi.org/10.1001/jamanetworkopen.2020.8857
Caly, L., Druce, J. D., Catton, M. G., Jans, D. A., Wagstaff, K. M. (2020). The FDA-approved drug ivermectin inhibits the replication of SARS-CoV-2 in vitro. Antiviral Research, 178, 104787. https://doi.org/10.1016/j.antiviral.2020.104787
Cao, B., Wang, Y., Wen, D. (2020). A trial of lopinavir-ritonavir in adults hospitalized with severe Covid-19. New England Journal of Medicine, 382(19), 1787-1799. https://doi.org/10.1056/NEJMoa2001282
Cavalli, G., De Luca, G., Campochiaro, C. (2020). Interleukin-1 blockade with high-dose anakinra in patients with COVID-19, acute respiratory distress syndrome, and hyperinflammation: A retrospective cohort study. The Lancet Rheumatology, 2(6), e325-e331. https://doi.org/10.1016/S2665-9913(20)30127-2
Chorin, E., Dai, M., Shulman, E. (2020). The QT interval in patients with COVID-19 treated with hydroxychloroquine and azithromycin. Nature Medicine, 26(6), 808-809. https://doi.org/10.1038/s41591-020-0888-2
(2020). Combined list of drugs that prolong QT and/or cause torsades de pointes (TDP)..
El-Senousey, H., Chen, B., Wang, J., Atta, A., Mohamed, F., Nie, Q. (2018). Effects of dietary vitamin C, vitamin E, and alpha-lipoic acid supplementation on the antioxidant defense system and immune-related gene expression in broilers exposed to oxidative stress by dexamethasone. Poultry Science, 97(1), 30-38. https://doi.org/10.3382/ps/pex281
Eltahan, N., Elsawy, N., Abdelaaty, K. (2024). Atorvastatin for reduction of 28-day mortality in severe and critical COVID-19 patients: a randomized controlled trial. Respir Res., 25, 97. https://doi.org/10.1186/s12931-024-02732-2
Fang, L., Karakiulakis, G., Roth, M. (2020). Are patients with hypertension and diabetes mellitus at increased risk for COVID-19 infection?. The Lancet Respiratory Medicine, 8(4), e21. https://doi.org/10.1016/S2213-2600(20)30116-8
Fedson, D. S., Opal, S. M., Rordam, O. M. (2020). Hiding in plain sight: An approach to treating patients with severe COVID-19 infection. mBio, 11(2), e00398-20. https://doi.org/10.1128/mBio.00398-20
(2020). FDA advises patients on use of non-steroidal anti-inflammatory drugs (NSAIDs) for COVID-19..
Gautret, P., Lagier, J., Parola, P., Meddeb, L., Mailhe, M., Doudier, B. (2020). Hydroxychloroquine and azithromycin as a treatment of COVID-19: Results of an open-label non-randomized clinical trial. International Journal of Antimicrobial Agents, 56(1), 105949. https://doi.org/10.1016/j.ijantimicag.2020.105949
Goldman, J. D., Lye, D. C., Hui, D. S. (2020). Remdesivir for 5 or 10 days in patients with severe COVID-19. New England Journal of Medicine, 383(19), 1827-1837. https://doi.org/10.1056/NEJMoa2015301
Hassan, A., Hegazy, S., Radwan, S. (2022). Clinical study to evaluate the possible efficacy and safety of antibodies combination (casirivimab and imdevimab) versus standard antiviral therapy as antiviral agent against Corona virus 2 infection in hospitalized COVID-19 patients. medRxiv. https://doi.org/10.1101/2022.08.20.22279020
Hassan, A., Hegazy, S., Radwan, S. (2023). Clinical study to evaluate the possible efficacy and safety of antibodies combination (casirivimab and imdevimab) versus standard antiviral therapy as antiviral agent against Corona virus 2 infection in hospitalized COVID-19 patients. Res Square.. https://doi.org/10.21203/rs.3.rs-1991618/v2
Hegazy, S., Hassan, A. (2024). Comparing the efficacy of remdesivir, favipiravir, and casirivimab and imdevimab on duration of hospitalization and ICU stay of hospitalized COVID-19 patients. Life Sci Res Commun., 1(1), 21-30.
Hegazy, S., Tharwat, S., Hassan, A. (2023). Clinical study to compare the efcacy and safety of casirivimab and imdevimab, remdesivir, and Favipiravir in hospitalized COVID-19 patients. J Clin Virol Plus., 3(2), 100151. https://doi.org/10.1016/j.jcvp.2023.100151
Hegazy, S., Tharwat, S., Hassan, A. (2023). Comparing the efficacy of regen-cov, remdesivir, and favipiravir in reducing invasive mechanical ventilation need in hospitalized COVID-19 patients. World J Clin Cases., 11(26), 6105.
Hegazy, S., Tharwat, S., Hassan, A. (2023). Study to compare the effect of casirivimab and imdevimab, remdesivir, and favipiravir on progression and multi-organ function of hospitalized COVID-19 patients. Open Medicine, vol. 18(no. 1), 20230768. https://doi.org/10.1515/med-2023-0768
Horby, P., Lim, W. S., Emberson, J. (2020). Effect of dexamethasone in hospitalized patients with COVID-19: Preliminary report. medRxiv. https://doi.org/10.1101/2020.06.22.20137273
Kaiser, U. B., Mirmira, R. G., Stewart, P. M. (2020). Our response to COVID-19 as endocrinologists and diabetologists. Journal of Clinical Endocrinology and Metabolism, 105(5), dgaa148. https://doi.org/10.1210/clinem/dgaa148
Kim, U. J., Won, E., Kee, S., Jung, S., Jang, H. (2016). Combination therapy with lopinavir/ritonavir, ribavirin and interferon-α for Middle East respiratory syndrome. Antiviral Therapy, 21(5), 455-459. https://doi.org/10.3851/IMP3002
Kuba, K., Imai, Y., Rao, S., Gao, H., Guo, F., Guan, B. (2005). A crucial role of angiotensin-converting enzyme 2 (ACE2) in SARS coronavirus-induced lung injury. Nature Medicine, 11(8), 875-879. https://doi.org/10.1038/nm1267
Molina, J. M., Delaugerre, C., Le Goff, J., Mela-Lima, B., Ponscarme, D., Goldwirt, L. (2020). No evidence of rapid antiviral clearance or clinical benefit with the combination of hydroxychloroquine and azithromycin in patients with severe COVID-19 infection. Médecine et Maladies Infectieuses, 50(4), 384. https://doi.org/10.1016/j.medmal.2020.03.006
Patel, A. B., Verma, A. (2020). COVID-19 and angiotensin-converting enzyme inhibitors and angiotensin receptor blockers: What is the evidence?. JAMA, 323(18), 1769-1770. https://doi.org/10.1001/jama.2020.4812
(2020). Tocilizumab improves significantly clinical outcomes of patients with moderate or severe COVID-19 pneumonia. PR Newswire..
Richardson, P., Griffin, I., Tucker, C. (2020). Baricitinib as potential treatment for 2019-nCoV acute respiratory disease. The Lancet Rheumatology, 2(2), e30-e31. https://doi.org/10.1016/S2665-9913(20)30016-2
Rosa, S. G. V., Santos, W. C. (2020). Clinical trials on drug repositioning for COVID-19 treatment. Revista Panamericana de Salud Pública, 44, e40. https://doi.org/10.26633/RPSP.2020.40
Sachse, G., Willms, B. (1980). Efficacy of thioctic acid in the therapy of peripheral diabetic neuropathy. Hormone and Metabolic Research Supplement Series, 9, 105-107.
Hegazy, S. K. (2024). The efect of combination treatment with casirivimab and imdevimab versus standard antiviral therapy on clinical outcomes in hospitalized COVID-19 patients. Discover, 1(71).). https://doi.org/10.1007/s44337-024-00045-3
Savarino, A., Boelaert, J. R., Cassone, A., Majori, G., Cauda, R. (2003). Effects of chloroquine on viral infections: An old drug against today's diseases. The Lancet Infectious Diseases, 3(11), 722-727. https://doi.org/10.1016/S1473-3099(03)00806-5
Sciascia, S., Aprà, F., Baffa, A. (2020). Pilot prospective open, single-arm multicentre study on off-label use of tocilizumab in patients with severe COVID-19. Clinical and Experimental Rheumatology, 38(3), 529-532.
Shakoory, B., Carcillo, J. A., Chatham, W. W. (2016). Interleukin-1 receptor blockade is associated with reduced mortality in sepsis patients with features of macrophage activation syndrome: Reanalysis of a prior Phase III trial. Critical Care Medicine, 44(2), 275-281. https://doi.org/10.1097/CCM.0000000000001402
Sheahan, T. P., Sims, A. C., Leist, S. R., Schäfer, A., Won, J., Brown, A. J. (2020). Comparative therapeutic efficacy of remdesivir and combination lopinavir, ritonavir, and interferon beta against MERS-CoV. Nature Communications, 11(1), 222. https://doi.org/10.1038/s41467-019-13940-6
Tsang, K., Zhong, N. S. (2003). SARS: Pharmacotherapy. Respirology, 8(Suppl. 1), S25-S30. https://doi.org/10.1046/j.1440-1843.2003.00522.x
Tibullo, D., Volti, G. L., Giallongo, C., Grasso, S., Tomassoni, D., Anfuso, C. D. (2017). Biochemical and clinical relevance of alpha lipoic acid: Antioxidant and anti-inflammatory activity, molecular pathways and therapeutic potential. Inflammation Research, 66(11), 947-959. https://doi.org/10.1007/s00011-017-1079-8
Vincent, M. J., Bergeron, E., Benjannet, S., Erickson, B. R., Rollin, P. E., Ksiazek, T. G. (2005). Chloroquine is a potent inhibitor of SARS coronavirus infection and spread. Virology Journal, 2(1), 69. https://doi.org/10.1186/1743-422X-2-69
Wang, X., Guo, X., Xin, Q. (2020). Neutralizing antibody responses to SARS-CoV-2 in COVID-19 inpatients and convalescent patients. medRxiv.. https://doi.org/10.1101/2020.04.22.20075091
(2020). Situation report - 193..
Wu, C. J., Jan, J. T., Chen, C. M., Hsieh, H. P., Hwang, D. R., Liu, H. W. (2004). Inhibition of severe acute respiratory syndrome coronavirus replication by niclosamide. Antimicrobial Agents and Chemotherapy, 48(7), 2693-2696. https://doi.org/10.1128/AAC.48.7.2693-2696.2004
Wu, Y., Tseng, C., Cheng, M., Ho, H., Shih, S., Chiu, D. T. (2008). Glucose-6-phosphate dehydrogenase deficiency enhances human coronavirus 229E infection. Journal of Infectious Diseases, 197(6), 812-816. https://doi.org/10.1086/528377
Yamamoto, N., Yang, R., Yoshinaka, Y., Amari, S., Nakano, T., Cinatl, J. (2004). HIV protease inhibitor nelfinavir inhibits replication of SARS-associated coronavirus. Biochemical and Biophysical Research Communications, 318(3), 719-725. https://doi.org/10.1016/j.bbrc.2004.04.083
Ye, M., Fu, D., Ren, Y., Wang, F., Wang, D., Zhang, F. (2020). Treatment with convalescent plasma for COVID-19 patients in Wuhan, China. Journal of Medical Virology, 92(10), 1858-1865. https://doi.org/10.1002/jmv.25882
Zeng, Q., Yu, Z., Gou, J. (2020). Effect of convalescent plasma therapy on viral shedding and survival in COVID-19 patients. Journal of Infectious Diseases, 222(1), 38-43. https://doi.org/10.1093/infdis/jiaa228
Zhang, L., Liu, Y. (2020). Potential interventions for novel coronavirus in China: A systematic review. Journal of Medical Virology, 92(5), 479-490. https://doi.org/10.1002/jmv.25707
Zhang, X. W., Yap, Y. L. (2004). Old drugs as lead compounds for a new disease? Binding analysis of SARS coronavirus main proteinase with HIV, psychotic and parasite drugs. Bioorganic and Medicinal Chemistry, 12(10), 2517-2521. https://doi.org/10.1016/j.bmc.2004.03.035
Acknowledgments
None.
Conflict of Interest
The author declares that there is no conflict of interest.